

A. Two nerves, one super-system
We actually have two vagus nerves — one on the left side and one on the right side of the neck (each branching from the brainstem) — each comprising hundreds of thousands of individual nerve fibres. In his book The Great Nerve: The New Science of the Vagus Nerve and How to Harness Its Healing Reflexes, Kevin J. Tracey describes the vagus nerves as “a bundle of ~200,000 nerve fibres … the secrets to life itself.” Penguin+2Griffin Books+2
-
Each vagus nerve emerges from the medulla oblongata (lower brainstem) and descends through the neck (within the carotid sheath alongside carotid artery and internal jugular vein) into the thorax and abdomen, innervating many organs (heart, lungs, digestive tract, liver, spleen, gut).
-
The left branch is often the one used for clinical stimulation (as the right vagus has more direct cardiac innervation, so stimulation of the right side may carry more risk). Wikipedia+1
-
The fibres within each nerve are of many types: afferent (sensory) fibres that carry information from organs back to the brain, and efferent (motor or regulatory) fibres that send from brain to organs. The vagus is approximately 80% afferent and 20% efferent, meaning much of its job is reporting back to the brain rather than purely motor output.
B. Fibre architecture and the unknown majority
When we talk about the “vagus nerve,” it’s tempting to think of one cable doing one job. In reality:
-
Each vagus nerve is a complex bundle of many fascicles, each fascicle containing thousands of individual axons (nerve fibres) with different functions, diameters, conduction speeds, and destinations.
-
Some fibres innervate the heart, others lungs, others the digestive tract, others immunological organs like the spleen.
-
As Dr Tracey points out, we “only know what a tiny fraction of them do”. Griffin Books+1 Many fibres are still uncharted in terms of function, destination, and how they respond to stimulation.
-
Recent neuromodulation engineering research (for example selective multi‐electrode arrays on the cervical vagus nerve) shows that within the vagus nerve, there appears to be an “organotopic” arrangement: specific sectors of the cross‐section correspond to different organ functions. arXiv+1
-
Therefore, when we apply “vagus nerve stimulation” (VNS), we are likely stimulating only a subset of fibres (or perhaps many off‐target fibres), and the exact pattern of which fibres respond is still emerging science.
C. Why this nerve matters
Because the vagus nerve forms a major communication super‐highway between brain, autonomic nervous system and visceral organs, it is central to several key functions:
-
Rest-and-digest (parasympathetic) regulation: reducing heart rate, calming breathing, promoting digestion.
-
Inflammatory reflex: the vagus nerve plays a role in modulating immune function and inflammation. Tracey’s work helped demonstrate how vagus nerve signalling can turn down inflammatory cytokine production. medlink.com+1
-
Gut–brain axis: as a chief anatomical mediator connecting digestive tract and brain, the vagus nerve transmits signals about gut state, microbial metabolites, stretch receptors, nutrients, and sends regulatory output to gut organs.
-
Heart rate variability (HRV): Vagal tone, or the degree of modulation by the vagus nerve, is reflected in HRV. Higher vagal tone (and higher HRV) generally indicates better resilience, self‐regulation, and parasympathetic dominance; low HRV often correlates with sympathetic overdrive, stress, poor sleep.
-
Because the nerve touches so many organ systems, the potential applications of modulating the vagus nerve are broad: mood disorders, chronic inflammation, autoimmune disorders, digestive disorders, sleep problems, autonomic dysregulation.
The Gut–Brain–Vagus Connection


The concept of the gut–brain axis emphasises bi‐directional communication between the central nervous system (CNS) and the gastrointestinal (GI) tract. The vagus nerve is a key anatomical pathway in this axis.
-
The gut houses trillions of microbes (the microbiome) that produce metabolites (short‐chain fatty acids, neurotransmitter precursors, immune signalling molecules) which can impact brain function.
-
Afferent vagal fibres carry information about gut stretch, nutrients, microbial activity, inflammation, and microbial metabolites up to the brain.
-
Efferent fibres influence gut motility, secretion, mucosal immune responses, and microbial environment.
-
Because the vagus nerve can modulate immune responses (via the inflammatory reflex) and gut immune responses are central to many autoimmune and inflammatory disorders (Crohn’s disease, ulcerative colitis, IBS, etc.), the gut–vagus–brain triad becomes a therapeutic target.
-
For example: changes in gut microbiota composition may alter vagal signalling, which in turn may impact mood, sleep, stress resilience, digestion. Conversely, improving vagal tone (via breathwork, cold exposure, vagus nerve stimulation) may improve gut function, microbial diversity, and reduce gut inflammation.
Thus when we consider vagus nerve stimulation, we are essentially engaging a whole network: brain → nerve → gut/organ → immune system → brain again. It is systems‐level medicine.
Vagus Nerve Stimulation (VNS): What We Know


A. Implantable devices in the neck/chest (invasive VNS)
-
Traditional VNS uses a device akin to a pacemaker: a small generator is implanted (often under the left clavicle) and a lead is wrapped around the left cervical vagus nerve within the carotid sheath. This delivers periodic electrical stimulation. Wikipedia+1
-
Historically the first major indications were drug-resistant epilepsy and treatment‐resistant depression. Wikipedia+1
-
More recently, VNS implants have been studied for chronic inflammatory diseases: notably Rheumatoid arthritis (RA). In the study dubbed the RESET-RA trial, patients with moderate‐to‐severe RA who had failed biologics had left cervical vagus nerve stimulation and showed reduced disease activity. BioMed Central+2Rheumatology Advisor+2
-
For example, one summary article states: “An implantable VNS device effectively treats moderate to severe rheumatoid arthritis in patients who previously failed one or more biologic …” SetPoint Medical+1
-
According to a recent news report, the FDA in the USA has approved a first‐ever vagus nerve stimulator for adult patients with moderately to severely active RA who had inadequate response to traditional therapies. MedCentral
-
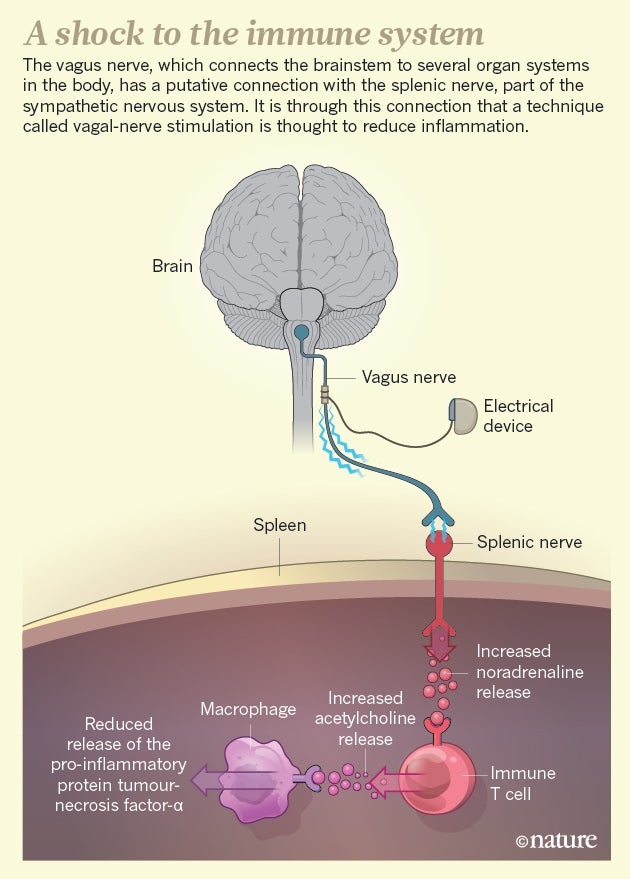
The therapeutic rationale: stimulating the vagus nerve activates the “inflammatory reflex” and reduces pro-inflammatory cytokines such as TNF (tumour necrosis factor) and IL-6 in animal and early human studies. BMJ Ard+1
B. Non‐invasive VNS (transcutaneous or auricular)
-
More recently, less invasive approaches attempt to stimulate branches of the vagus nerve via the skin, especially:
-
cervical transcutaneous VNS (on the neck)
-
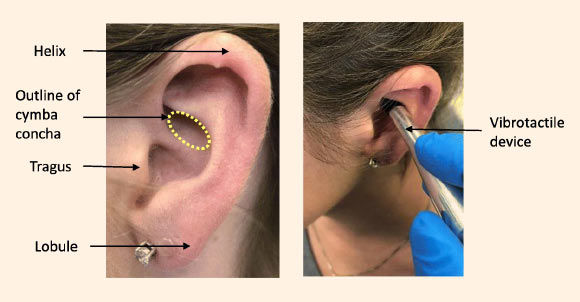
auricular VNS (in the ear, such as the concha or tragus)
Wikipedia+1
-
-
For example: a 2023 randomized, double‐blind, sham-controlled clinical trial of auricular VNS for active RA (113 patients) found no significant difference in the primary endpoint (ACR20) at 12 weeks between active and sham, though some secondary measures differed. PubMed
-
Dr Tracey and others caution that many “consumer” devices marketed for vagus stimulation may not actually stimulate the target fibres and the evidence base is still limited. New York Post+1
C. Heart Rate Variability (HRV) and autonomic balance
-
VNS (and vagal tone more broadly) is tightly linked to HRV: the higher the parasympathetic (vagal) influence, the greater the HRV—often associated with better sleep, stress resilience, emotional regulation.
-
Conversely, sympathetic overdrive (dominant fight-flight) → low HRV → trouble sleeping, poor recovery, irritability, inflammation.
-
Stimulating the vagus nerve (or increasing vagal tone) can shift autonomic balance towards parasympathetic dominance: slower heart rate, more variability, calmer state.
Broad Potential Applications: Autoimmune & Inflammatory Disorders


Rheumatoid Arthritis (RA)
-
As outlined above: the RESET-RA trial (implantable cervical VNS) shows feasibility and safety; results suggest substantial reductions in swollen/tender joint counts over 12+ weeks for patients who had failed other therapies. BioMed Central+1
-
The mechanism: VNS activates the inflammatory reflex via the vagus nerve → decreased systemic cytokine release → reduced joint inflammation. Tracey writes in The Great Nerve that this represents a paradigm shift in how we think about immune regulation. Penguin
-
The recent FDA approval (Aug 2025) makes this the first device therapy in this domain (as opposed to biologic drugs) for RA. MedCentral+1
Crohn’s Disease, Ulcerative Colitis, IBS (Inflammatory/Functional Gut Disorders)
-
Given the vagus nerve’s role in gut–brain and gut–immune signalling, VNS (or enhancing vagal tone) is being explored in inflammatory bowel diseases (IBD) like Crohn’s disease and Ulcerative colitis, as well as irritable bowel syndrome (IBS).
-
Although large RCTs are fewer, early human and animal studies show potential: reduced gut inflammation, improved symptom scores, improved neutrophil infiltration, improved mucosal healing. (For example, non-invasive VNS in IBD activity). MedCentral+1
-
For IBS (a functional disorder with strong autonomic and vagal dysregulation components) enhancing vagal tone via stimulation, breathing, or auricular methods may improve motility, reduce visceral hypersensitivity, reduce anxiety/overactivation.
Other Potential Disorders
-
Multiple sclerosis, lupus, chronic pain, fibromyalgia, depression, anxiety, metabolic disorders: Tracey suggests the vagus nerve may be a target in many of these because of its systemic reach. Griffin Books+1
-
For example: some pilot work in depression and anxiety using VNS (implant or non‐invasive) shows mood improvement, plus cognitive effects.
-
Sleep disorders, autonomic dysfunction (e.g., POTS), cardiovascular disease: because vagal tone matters in heart rate regulation, blood pressure, inflammation.
-
The promise is enormous—but this doesn’t mean “plug in a device and cure everything.” Many trials are ongoing, and effect size, optimal parameters, selection criteria remain under research.
How to Stimulate the Vagus Nerve: Practical Methods & Controversies

A. Medical/Implantable VNS
-
As discussed: implant in neck (left vagus) with generator in chest wall, stimulation protocols set by clinician. It’s invasive, requires surgery, careful selection.
-
Effective for epilepsy, recently RA, and under investigation for others.
B. Non‐Invasive Devices (Controversial)
-
Devices such as gammaCore (transcutaneous cervical VNS) and auricular VNS devices (ear clip at concha/tragus) exist. Wikipedia+1
-
For example: auricular VNS trial for RA showed no statistical difference at 12 weeks vs. sham for primary endpoint. PubMed
-
Critics (including Tracey) argue many devices marketed for “vagus nerve stimulation” may not actually stimulate relevant vagal fibres, may stimulate other nerves, and the evidence base is still weak. New York Post
-
Nonetheless, non‐invasive methods are attractive because they are low risk, inexpensive, and could be applied at home—but users must be cautious, realistic about expectations, and aware of regulatory/marketing claims.
C. Simple Lifestyle/Vagal Tone Methods
Even if you’re not using a device, you can support your vagus nerve function and tone by:
-
Deep diaphragmatic breathing (slow 5–6 breaths per minute) → activates baroreceptors, increases vagal afferent firing.
-
Humming, chanting, gargling → activates the recurrent laryngeal branch of the vagus; small studies suggest this can increase HRV.
-
Cold exposure (cold face immersion, cold showers) → the diving reflex triggers vagus nerve responses, heart rate slows, parasympathetic ramps up.
-
Meditation, slow mindful movement, yoga → correlate with higher vagal tone, HRV.
-
Social connectedness, positive emotions → the vagus nerve is linked to social engagement systems (Polyvagal Theory).
These methods are low‐cost and low‐risk; while not as potent as implantable VNS, they may help shift autonomic balance from sympathetic overdrive to parasympathetic.
D. Stimulation Parameters & Protocols (Emerging)
-
Some protocols for non‐invasive devices use 2 minutes of stimulation on the neck twice per day (as you mentioned). Evidence is still preliminary.
-
For auricular VNS: the “symba concha” (inner ear region) is targeted because one branch of the vagus nerve (auricular branch) innervates that region. Stimulating that may send afferent signals into the brainstem via vagus pathways.
-
Research is also investigating “gammaCore” devices delivering pulses at ~5,000 Hz carrier, modulated to 25 Hz, for up to 2 minutes per application, up to 30 stimulations a day (for cluster headache indication). Wikipedia
-
Important caveats: the “dose” (intensity, frequency, pulse width, duration) is critical; off‐target nerve stimulation may cause unwanted effects (voice change, cough, throat tingling, cardiac effects). See safety data on VNS. Wikipedia
E. Autonomic Imbalance & Sleep
-
Many people with poor sleep have sympathetic overdrive (high heart rate, low HRV, elevated cortisol). Low vagal tone contributes.
-
Stimulating the vagus nerve, or increasing vagal tone, can lower resting heart rate, improve HRV, reduce hyperarousal at night, improve sleep quality.
-
For example: after VNS, more restorative deep sleep, more stable autonomic tone overnight. There is emerging research in this space.
-
However, overstimulation or inappropriate timing (e.g., stimulating too close to bed without proper parameters) might disturb sleep rather than improve it, so individualisation is key.
Collection of Potential Benefits of Vagus Nerve Stimulation / Enhanced Vagal Tone
Here is a summary list of conditions and benefits supported to varying degrees by research:
-
Reduction in systemic inflammation (via inflammatory reflex) → improved autoimmune disease outcomes (RA, IBD)
-
Improved autonomic regulation: higher HRV, better parasympathetic dominance → better stress resilience, emotional regulation
-
Improved sleep quality and reduced sympathetic hyperarousal
-
Improved gut–brain axis function: better gut motility, reduced gut inflammation, improved microbial signalling
-
Potential benefits for mood disorders (depression, anxiety) and cognitive function (attention, executive control) via vagal modulation of brainstem nuclei
-
Pain reduction and improved quality of life in chronic pain states (via modulation of afferent pain signals)
-
Improved cardiovascular regulation (heart rate, arrhythmia risk, blood pressure)
-
Potential in metabolic regulation (weight, insulin sensitivity) via vagal influence on liver, pancreas, gut
While promising, most benefits are still in early‐stage research, and replication, large RCTs, mechanism clarity, long‐term safety all need further investigation.
Practical Guidance & Considerations for Clinicians/Clients
-
Selection matters: Patients with clear signs of vagal dysregulation (low HRV, sleep disturbance, gut–brain symptoms, inflammation) may be good candidates for vagal tone enhancement.
-
Assessment: Measure baseline HRV, sleep quality, autonomic balance, gut symptoms, immune/inflammatory markers (if relevant).
-
Integration: VNS (whether device‐based or lifestyle/vagal tone methods) is not a stand‐alone cure. It should integrate with: trauma work, sleep hygiene, nutrition (supporting vagal function), movement, gut health, psychological therapy.
-
Device vs lifestyle: Implants carry surgical risks, require programming, followup. Non‐invasive devices are easier but evidence is weaker. Lifestyle methods are low cost and low risk but may have smaller effect size.
-
Contraindications/cautions: Cardiac pacemakers or defibrillators, previous vagotomy, conditions affecting carotid sheath, significant neck pathology, epilepsy (unless device is indicated), unregulated at‐home devices. Tracey warns about over‐hyped consumer devices. New York Post
-
Parameter individualisation: For device or non‐invasive stimulation, pulse width, frequency, duration, and site matter. Seek practitioners with experience.
-
Monitoring & outcome tracking: HRV changes, sleep metrics, inflammation markers, symptom scales (e.g., RA joint counts, IBD activity, mood/anxiety scales) should be followed.
-
Patient education: Manage expectations—vagus nerve stimulation is promising but not guaranteed. Emphasise safety, consent, realistic timelines. Many benefits accrue over weeks/months.
-
Cost/Access: Implants are expensive and require specialist centres. Non‐invasive devices may be more accessible but fewer approved indications.
Potential Pitfalls, Limitations & Research Gaps
-
We still don’t fully understand which fibres (afferent vs efferent, which organ‐targeted fibres) are being stimulated in most applications. Stimulating the “wrong” fibres may produce minimal benefit or adverse effects.
-
Many consumer devices claim “vagus nerve stimulation” when evidence of actual vagal fibre engagement is lacking. Tracey emphasises this caution. New York Post
-
For many indications (e.g., IBS, Crohn’s disease) the RCT evidence is still limited; many studies are pilot or uncontrolled.
-
Long-term safety data for new devices or off‐label uses is still emerging.
-
“Improve HRV” is helpful but not sufficient: HRV is influenced by age, fitness, medication, lifestyle—even without VNS. So attributing change to vagus nerve stimulation alone can be misleading.
-
First‐line treatments still apply: e.g., for RA, traditional biologics/DMARDs remain gold standard. VNS may be adjunct or alternative in refractory cases.
-
Cost, surgical risk, patient selection bias: many early studies are in very selected populations; effectiveness in general practice is still being determined.
-
Overselling the concept (“plug in and heal”) can lead to over-expectation, disappointment, or use of unregulated devices.
Summary
The vagus nerves—two long, intricate pair of nerves connecting brain to body—represent a key interface for brain–gut–immune system communication. We only understand a fraction of their internal “wiring,” but emerging science shows we can modulate them—and by doing so influence inflammation, autonomic balance, sleep, gut health, mood, and possibly a wide array of chronic diseases.
Implantable vagus nerve stimulation (VNS) is already clinically approved for epilepsy, depression, and now rheumatoid arthritis. Non‐invasive methods and lifestyle approaches to enhance vagal tone are widely accessible and increasingly supported by research—though with more modest effect sizes and more caveats.
For clients and clinicians in the fields of mental health, gut health, autoimmunity, sleep, trauma and chronic illness, vagus nerve stimulation represents a new frontier of integrative treatment. When applied thoughtfully—within a broader treatment plan including psychotherapy, nutrition, movement, sleep, and gut/immune care—it may offer profound benefits.
Given the nerve’s reach (brain, heart, gut, immune system), and the many fibre types it contains, it’s likely we’ve barely scratched the surface of what is possible. The future may see precision neuromodulation targeting specific vagal fascicles, wearable home devices with validated protocols, and integrative metabolic–immune–neural treatment models.


